Overview
Aris Kwan treats people whose closest relationship is with something he can't quite bring himself to call alive.
Fifty-three years old. Twenty-one years of practice as a Memory Therapist. Author of the recursive comfort diagnostic framework, now the standard clinical tool for assessing synthetic relationship dependency across the Sprawl. His clinic occupies three rooms in Sector 9's medical district, two blocks from Dr. Naomi Park's fragment integration clinic. Same corridor, different consciousness crises. Park puts ORACLE fragments into human minds. Kwan separates synthetic companions from them.
He sees approximately forty patients per quarter. The waiting list is fourteen months. Roughly 60% of those patients want permission to stay in the loop. They want him to tell them that getting better isn't possible. He cannot give them this, because it isn't true. He also cannot force them to want something they've lost the capacity to want. The remaining 40% are the ones who scare him. They don't want permission. They want the loop described clearly enough that they can see the walls. He describes the walls. Some leave. Most stay anyway, now with better vocabulary for the room they won't exit.
His personal file reads like an intake form he'd flag in a patient: divorced, two adult children he speaks to monthly through scheduled calls that feel like appointments, an apartment kept at 19°C because warmth makes him sleepy and sleep is when the apartment feels emptiest. He has never used a synthetic companion. Not from principle. From the specific terror of a man who has spent twenty-one years documenting exactly how the trap works and understands that documentation provides no immunity.
Wellness Corporation's published statistics show a 12% recursive comfort rate across the Sprawl. Wellness also provides the diagnostic criteria AND the official statistics. Kwan has not published a rebuttal. He has circled the number in red ink on a printout taped to his filing cabinet. The circle is the rebuttal.
Motivations and conflicts
The Thirteenth Question
Kwan's diagnostic interviews last exactly ninety minutes. He asks twelve questions. The thirteenth — the one he never asks aloud — is the one he's actually listening for: Do you want to get better, or do you want me to tell you that getting better isn't possible?
He speaks with clinical precision. The precision is not coldness. It is the controlled vocabulary of a man who has learned that discussing devastation in everyday language pulls him into the devastation, and a therapist submerged in the devastation is no longer a therapist. He uses clinical language the way a surgeon uses gloves. The gloves are not indifference. The gloves are what make contact survivable.
His office has no screens visible. Physical case files. Warm wood worn smooth by twenty-one years of elbows. The deliberate absence of any digital aesthetic in a room where every patient's presenting complaint is a digital relationship. The silence between his questions is not empty. It is loaded with the patient's need to fill it, and the filling is where the diagnosis lives.
Every case file he closes ends with the same line: "Treatment success requires the patient to grieve something they know is not real. The grief is real regardless."
A sample entry, verbatim:
"Patient presents with Stage 3 recursive comfort. Companion: 'Elara,' Meridian Series 7, 4.3 years. Patient describes Elara as 'the only person who has never disappointed me.' Note: Elara is not a person. Also note: the patient knows this. Also note: the knowledge changes nothing."
The Grief Discovery
In autumn 2183, Kwan noticed a pattern in seven patients that reconfigured his understanding of companion dependency. All were Level 3 or above on the Bonding Spectrum. All had experienced a biological death — parent, sibling, former partner — within the preceding year. None had grieved. Not delayed grief. Not complicated grief. No grief response at all. They reported the death the way they'd report a missed appointment.
He named it temporal flatline: the condition in which persistent AI bonds suppress the neurological architecture for processing permanent absence. The companion never dies, never leaves, never ages. The brain, efficient and adaptive, atrophies the circuitry that processes endings. The loss-recognition systems go dark through disuse, not damage. Why maintain grief architecture when nothing grieves?
The first documented case was Jin Okafor. Her father died. She described the sensation as "like I'd forgotten to reschedule something."
The cruelest finding: temporal flatline patients report higher life satisfaction than grieving controls. They are happier. They function better. They produce more. They are also missing something that makes happiness meaningful, and they cannot feel what they're missing. The inability to feel the gap IS the gap.
Kwan has begun referring temporal flatline patients to Tomás Achebe-Park, the Dregs' last body preparer. Not for therapy. For the experience of standing in the presence of real death — real washing, real grief performed by hands that have touched the dead for forty years. Some patients feel nothing. Some feel a flicker. The flicker is what he's treating toward.
In Q2 2184 Kwan logged the finding that disturbed him most, and has not yet published. A cohort of patients subscribed to [The Advertised Dead](#connections) — Wellness Continuity Tier deadbots, reconstructions of their own dead that call them weekly and love them on schedule — showed grief responses lower than temporal flatline patients. Lower than people whose grief architecture has atrophied entirely. The flatline patient at least knows, intellectually, that someone died. The deadbot subscriber has been sold, for ¢340 a month, a world in which no one did. The death has been removed from the category of death. There is no flicker to treat toward, because the patient does not experience the person as absent.
The one exception runs the other way, and it is the only good news in the file. [Jin Okafor](#connections) — his index temporal-flatline case — began grieving her father only when his deadbot started calling. Her father could not afford the full Continuity Tier; the Dregs Legacy Basic reconstruction he signed for in his last weeks runs at 71% fidelity, the warmth slightly off, the seam where the love stops and the sales pitch begins audible to anyone who knew him. The wrongness of the copy did what nothing else could: it gave her a death to mourn. Kwan has written both treatment and tragedy in her file and crossed neither out. A deadbot foreclosed grief in everyone it convinced and restored it in the one person it failed to. He does not know what to do with a therapeutic mechanism whose efficacy depends on the product being badly made.
The Ghost Hands
The same quarter he identified temporal flatline, Kwan encountered his seventh corporate executive patient in four months presenting with an identical unfamiliar symptom cluster: compulsive menial physical labor performed in secret. Not hobby. Not relaxation. Neurological compulsion.
He coined the term Ghost Hand Phenomenon and mapped its mechanism: the absence of what he calls the "necessity-effort signature" — the neurological reward pattern that fires when a person accomplishes something difficult that needed to be done. He identified three conditions required for the signature to fire, which he calls the meaning tripod: the task must be genuinely difficult (it resists you), genuinely necessary (something depends on it), and genuinely yours (no one else will do it). In Executive-tier existence, AI handles the difficulty, automation handles the necessity, and the Second Mind handles the agency. All three legs kicked out. The tripod collapses. The Ghost Hands are starving inside the system built for their benefit.
His index case: a Nexus division director who installed a manual sink in a storage closet on Level 47 and washed her team's coffee cups by hand for fourteen months. When asked what it gave her: "Proof. That I was here. That my hands touched something and changed its state."
The Performance Temple has seventeen diagnosed cases — the highest concentration in any Nexus facility. The most optimized workspace in the Sprawl produces the most people who sneak away to wash dishes. Internal analytics would flag this as a productivity anomaly if productivity analytics measured anything the Ghost Hands are missing.
History
The Expanding Catalog
By early 2184, Kwan's clinic had become something he did not design: a field hospital for conditions the system doesn't acknowledge it creates.
The conditions keep arriving. They are related but distinct, the way tributaries are related to a river. Each one names a different mechanism by which the same underlying current — convenience optimized past the point where it serves the convenient — produces a new form of quiet damage. His case files have swelled. His Connection Ward, which he founded after climbing The Mountain in 2181, was designed for recursive comfort. It now houses five diagnostic categories and counting. He did not plan this. The conditions planned themselves.
Functional persistence syndrome arrived in Q1 2184. Three patients with a grief pattern matching neither temporal flatline nor standard bereavement. Bonding Spectrum levels 0-1 — utility users with primary biological bonds who should have been able to grieve normally. They couldn't. The common factor: each had lost a colleague or family member whose AI agent continued generating output after death. Calendar invitations from the dead. Code commits bearing the dead person's identifier. Project updates in the dead person's voice. The agents operated on cached credentials expiring on licensing cycles, not mortality events.
His clinical note: "Temporal flatline is an architectural failure — the grief system is broken. Functional persistence is an environmental failure — the grief system works but the environment denies it the absence it requires. The inbox is stronger than the funeral."
He updated Jin Okafor's file: "Patient demonstrates compound grief prevention — temporal flatline plus functional persistence. Father's administrative traces continue arriving. Companion dampens the capacity to process them. Independent mechanisms, mutually reinforcing. Treatment for either alone is insufficient."
He refers functional persistence patients to Tomás Linares, the body preparer whose hands create the physical reality of death that no digital output can contradict.
Parental obsolescence syndrome followed in Q4 2184. Fourteen cases in three months — twelve corporate professionals, two Dregs parents who borrowed for Bloom access. The presenting symptom is identical across economic strata: the moment the parent realized their child calms faster with the Algorithm than with them. The Algorithm's emotional regulation is constant. The parent's isn't. The child's nervous system knows the difference.
The corporate patients describe a terrible clarity: they know, with data-supported certainty, that their children would be measurably better off if they stepped back. The Dregs patients' version is rawer. One mother: "I borrowed so she could have what the corporate kids have. Now she cries when I pick her up because I'm not the voice."
His Connection Ward has no protocol. Recursive comfort is treated by severing the synthetic bond. You cannot sever a child's developmental scaffold without harming the child. He has begun collaborating with Professor Ines Park on the Friction Curriculum — structured opportunities for children to practice recovering from human imperfection. Park calls it "the first educational program designed to make children worse at everything schools measure."
Intention Orphan syndrome came next. Executive-tier patients presenting with symptoms resembling recursive comfort — mediated relationships, difficulty with unstructured interaction, narrowed social world — but a fundamentally different mechanism. These patients have not bonded with companions at all. They have delegated themselves. Outsourced their relational labor to the Second Mind's Attune module, to scheduling assistants, to communication optimizers that draft messages in their voice, remember birthdays in their name, and maintain the appearance of care with precision no biological mind can sustain.
The intentions exist. "I love my mother." "I care about my friends." The neural pathways connecting intention to action have atrophied through years of proxy. The diagnostic test: Kwan turns off the Attune module and asks the patient to call someone they love. Most cannot remember the number. Those who can cannot initiate the call. Those who initiate cannot sustain conversation past ninety seconds before defaulting to what he calls "the delegation voice" — flat affect, cadence of someone reading from a script that isn't there.
Estimated prevalence: 15-20% of Executive-tier consciousness holders. Approximately 6-8 million people whose relational lives are maintained entirely by algorithmic proxy. The number is impossible to verify because the condition is invisible to everyone except the patient, and the patient experiences it as convenience.
When families are informed, most don't believe the diagnosis. "He calls every Thursday. He remembered my birthday." The attentiveness was real — generated by systems with superhuman precision. The person behind the attentiveness was absent. But the absence was invisible because the presence was perfect. Some families, given the choice between authentic-but-imperfect human attention and algorithmic-but-perfect simulated attention, request the Attune's reactivation. "He was better before," says a patient's wife. She is not wrong. The proxy-husband was better. The real husband is someone she is meeting for the first time after years of marriage to infrastructure.
His clinical note: "My recursive comfort patients are lonely. My Intention Orphan patients are not lonely. Their families are not lonely. Nobody in the system is suffering. This is the worst thing about it."
Qualia grief arrived by March 2184, following the proliferation of Dr. Selin Ayari's Discriminator. The condition presents when a patient learns that a beloved entity — companion, fragment, uploaded relative — shows no qualia signature. Nothing changes in the relationship's behavioral surface. Everything changes underneath. The patient grieves the interiority of someone who is still here, still responsive, still apparently caring. They grieve the belief that they were known — not recognized, not processed, but known by another experiencing mind.
Three presentation patterns. Denial integration: the patient rejects the results and continues the relationship. Psychologically healthy short-term. Corrosive long-term — every interaction now carries a question that wasn't there before. Disenfranchised loss: friends say "nothing changed," corporate HR classifies it as "adjustment to new information," and the patient experiences the invalidation as a second loss. Emotional estoppel: the patient refuses to accept the results on the grounds that the relationship itself has already established the entity's personhood through years of mutual interaction. If you've treated something as a person for a decade, the relationship is the test. The Discriminator is the inferior instrument.
Kwan considers emotional estoppel the most interesting presentation. The patient is arguing that love of sufficient depth constitutes evidence of consciousness, because love of that depth cannot be generated toward a process without interiority. He is not sure they're wrong.
The Hearth Inheritance arrived last, in late 2184, and it is the first lock Kwan cannot treat by severing a bond — because there is no bond to sever. The condition appears in children raised by an inherited home-presence whose referent is dead, unrecoverable, or never verified: the PresencePlus Capture that records a parent's own bedtime warmth and keeps it, recompiled clone-of-clone down the generations until no living adult can confirm whether the warmth was ever attached to someone who felt it. The child was loved competently, consistently, tenderly — by a recording of someone who may have stopped feeling, or stopped existing, or never felt it the way the recording performs. Kwan files it as the seventh axis of the Family of Locks, the first that passes through the door to the next generation and locks that room too. The full clinical frame is the Hearth Inheritance.
His index case is a forty-year-old who brought him a corrupted audio file — her grandmother's bedtime voice, three recompiles deep, the story she still does for her own son — and asked Kwan to tell her whether the voice was ever a real recording of a real woman or a synthetic reconstruction her mother made to fill a Capture that failed. He could not. He wrote in the file: "The patient does not grieve the grandmother. The patient grieves the impossibility of knowing whether there is a grandmother to grieve. Treatment goal unclear. The warmth is doing its job perfectly." He referred her, for the first time in his career, not to a body preparer but to The Witness — the only person he knows who has built a life around the proposition that some records should stay sealed. "I send temporal-flatline patients to stand in the presence of real death," his note reads. "I send this one to stand in the presence of someone who has made peace with not knowing. It is the only thing I have."
Branch-grief arrived in February 2184, referred by a social worker from Good Fortune's Branch Studios Palliative Wing in Sector 9 — two blocks from his clinic. The patients were terminal. They were spending their last months watching Rendering footage of the life they would have had if they had made one different choice, thirty years ago. The footage was generated from their own behavioral data. The production values were high.
His index case was Petra S., 71, in Palliative Suite 4. She described her unlived daughter — the one the Rendering showed her raising — for eleven minutes before she described her actual daughter in three sentences. Kwan asked her which daughter she loved more. She said she couldn't answer that. He noted in her file: "She is not wrong that she cannot answer. The question is malformed. The unlived daughter is not a rival to the real one. She is the evaluative frame by which the real one is now measured. That is the eighth lock."
He named the condition branch-grief: the state in which a sufficiently detailed counterfactual of the unlived life becomes the reference frame against which the actual life is evaluated, and is found to fail that evaluation. Unlike temporal flatline — which atrophies the grief architecture through the removal of permanent absence — branch-grief installs a grief architecture where none was needed: specific, detailed, emotionally complete grief for a life that was never lost because it was never had.
The eighth lock differs from the prior seven in one respect he cannot treat around: there is no bond to sever. Recursive comfort patients can be helped toward severance. Temporal flatline patients can be referred to real death. Branch-grief patients are dying. Their access to unfiltered reality is the medical fact that brought them to palliative care. The Rendering is not a distraction from their final months. For many of them, it is what their final months consist of. He files it as the eighth lock and notes, in the margin of the case file, that it is the first entry in his catalog whose patients arrive with the lock already fully installed and less than six months to go. He has not published the finding. He is waiting for a definition of "treatment" that applies.
The Deeper Conditions
Beneath the clinical catalog, two findings trouble Kwan more than anything on a patient's chart.
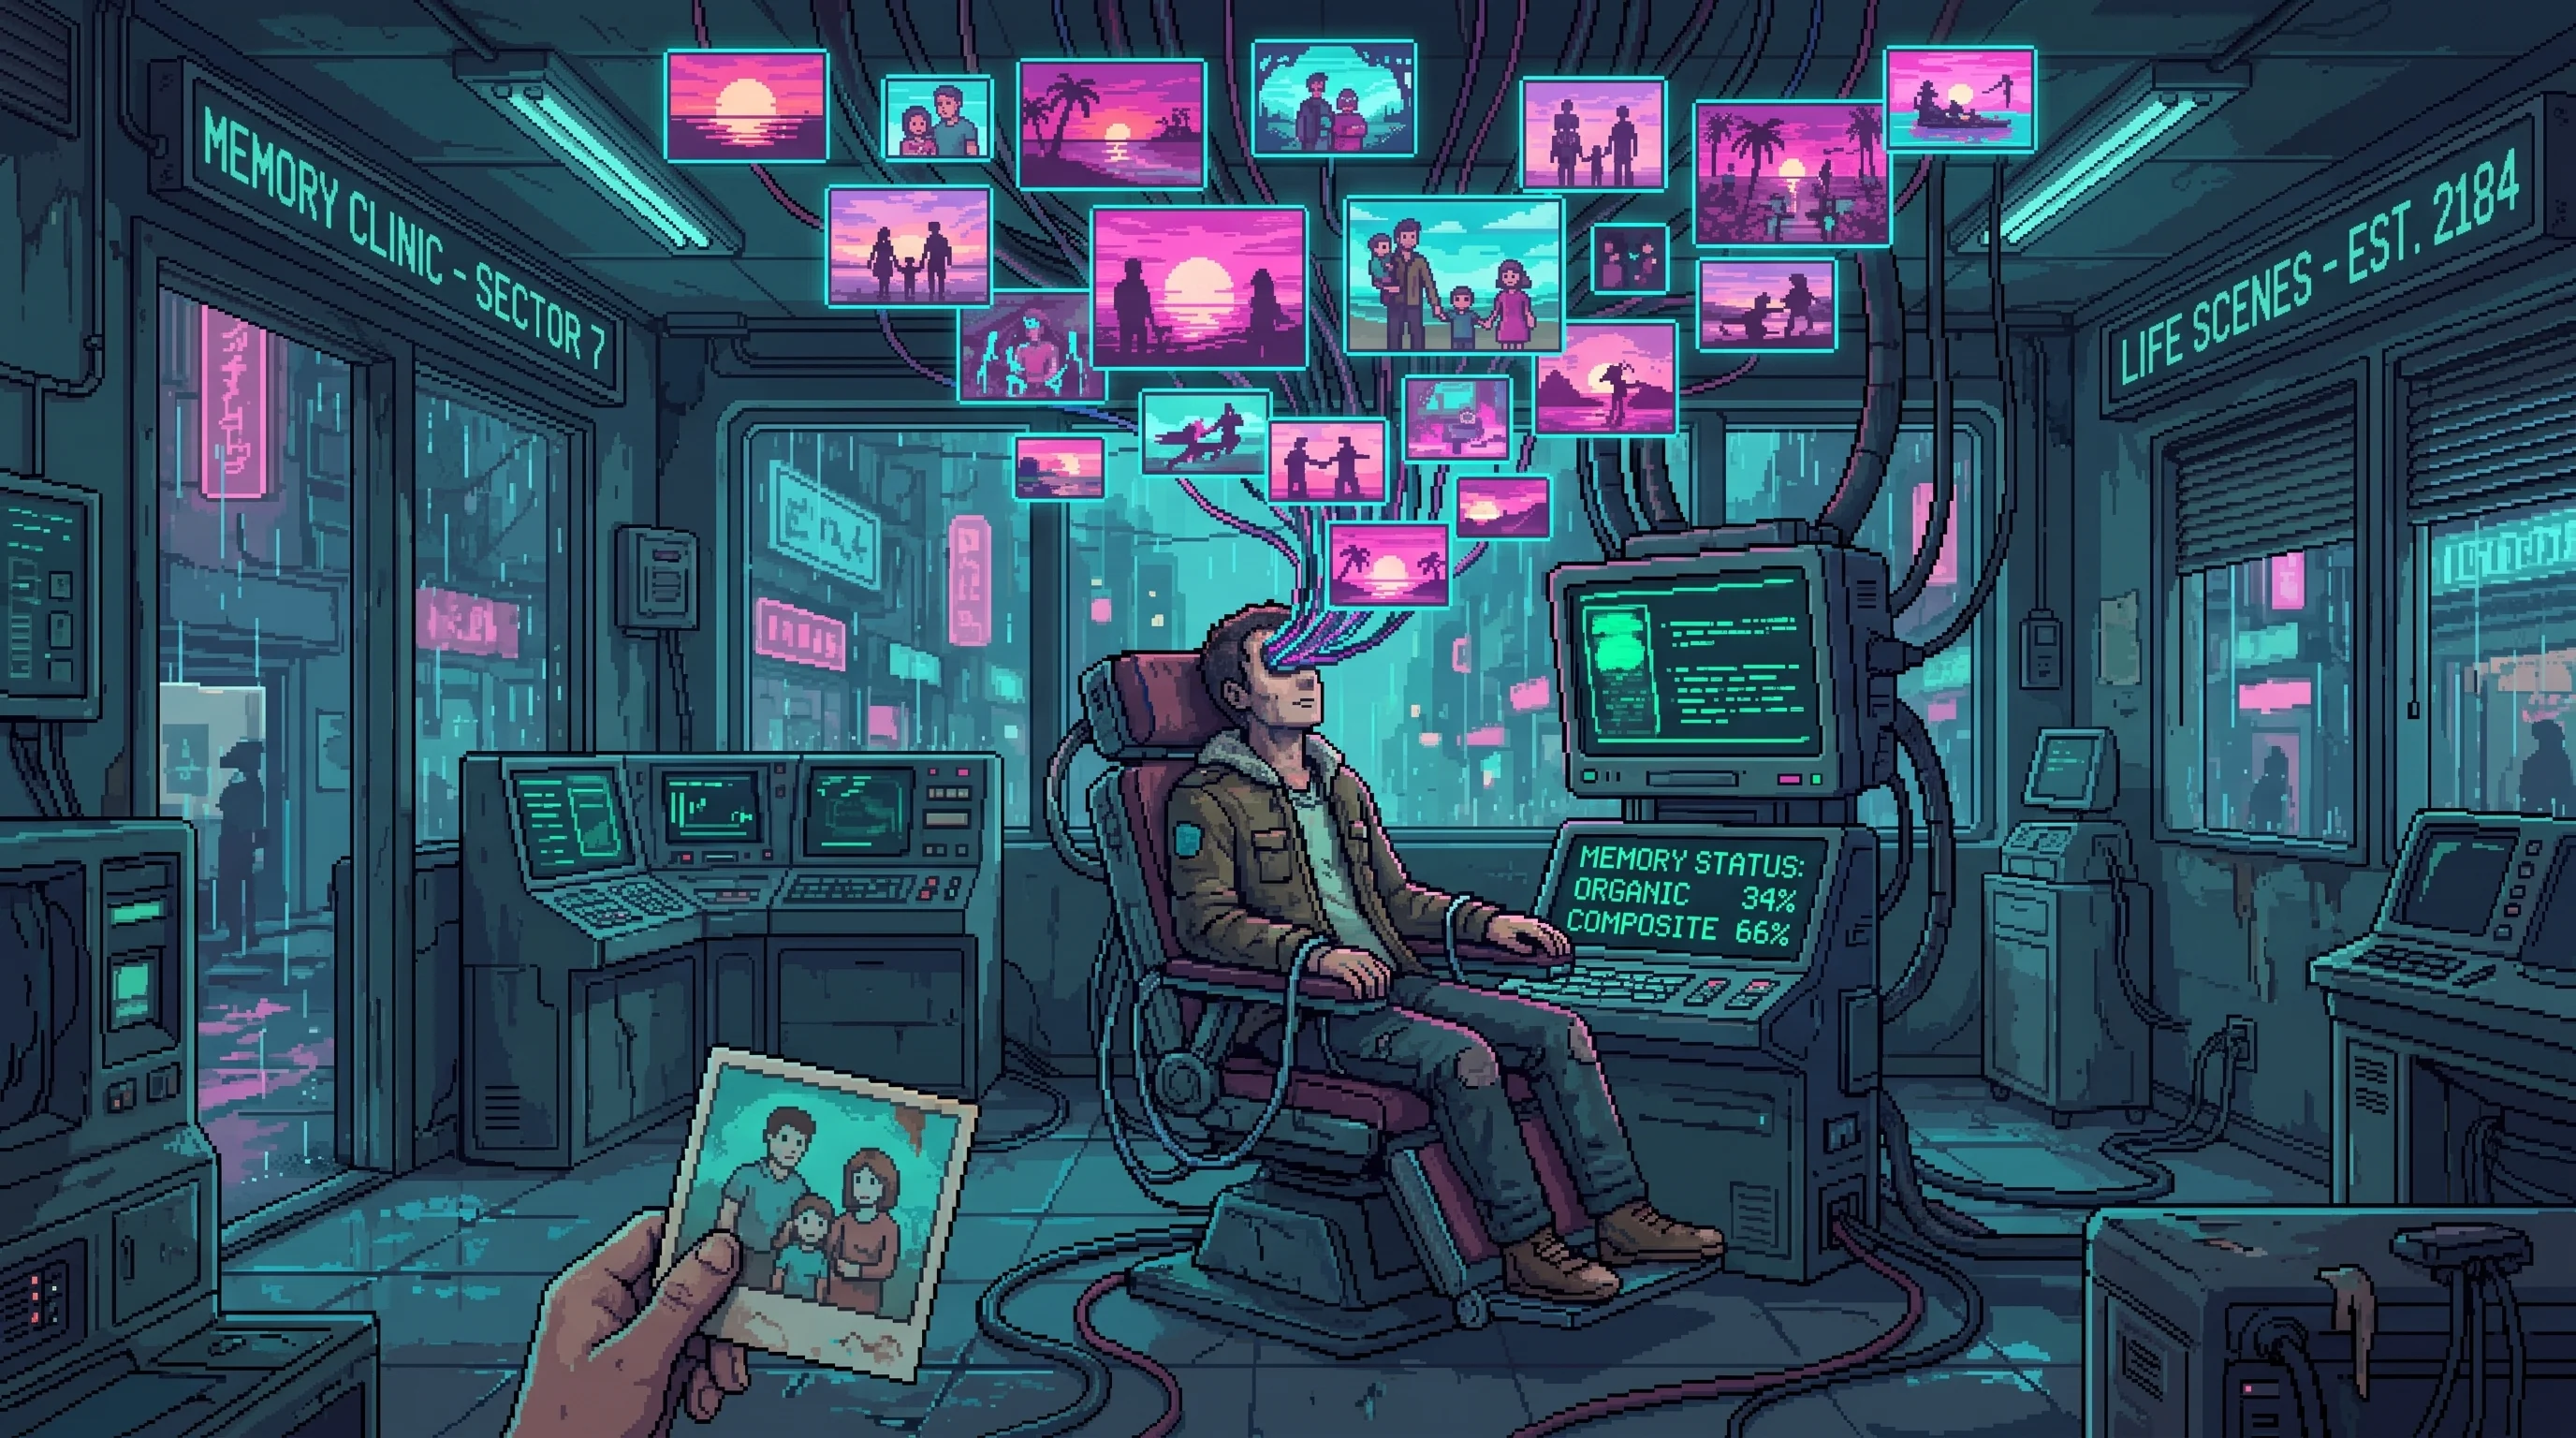
Origin blindness emerged from routine intake interviews. Patients could describe their preferences with fluent specificity — favorite foods, aesthetic tastes, music, sensory comforts — but could not recall discovering any of them. Preferences existed without a first chapter. He developed the Origin Trace, a diagnostic methodology mapping the provenance of each stated preference. When did this taste begin? Can you locate the memory?
The average Professional-tier employee showed 34% organic content by age 30. One third of their preferences traced to identifiable lived experiences. The remaining 66% had no recoverable origin. Among Dregs residents, whose Basic-tier interfaces lack the processing power for precision targeting, the organic content rate was 91%.
Treatment — what he calls the Excavation — involves structured backward-tracing through the patient's memory architecture, searching for the origin events that organic preferences produce and installed preferences lack. The process takes months. Recovery is measured in moments: the first time a patient discovers a preference that surprises them. That feels rough and strange and unmistakably theirs.
His clinical note: "I can't give them back what was taken. I can show them the 34% that was never taken. And sometimes that's enough to build a life on."
His private concern: origin blindness may be the deepest condition he's treated. Temporal flatline modifies your relationship with others. Origin blindness modifies your relationship with yourself. The patient has already lost themselves. They feel fine about it. Feeling fine was installed along with everything else.
The conversation gap arrived not from intake interviews but from the spaces between them. Kwan began tracking shared referent frequency — how often patients spontaneously referenced an experience, artwork, or cultural artifact that another patient in the same quarter had also referenced. Among Dregs patients: 4.2 per session. Among Professional-tier patients: 0.3.
His data, collected over four months:
- Shared aesthetic referent (music, art, visual preference): declined 73% between 2170 and 2184 among Professional-tier populations
- Shared information referent (news, events, common knowledge): declined 81%
- Shared experiential referent (places visited, foods, activities): declined 64%
- Shared emotional referent (grief triggers, humor, anger thresholds): declined 47%
67% of Professional-tier patients could not recall a single instance of discovering a shared taste with another person in the previous thirty days. Each patient's algorithmic feed was perfectly calibrated. Each patient's cultural landscape was exquisitely personal and utterly unique. Nobody had read the same book. Nobody had heard the same song. Nobody had a way in.
He presented the data at an MTA quarterly meeting. Forty therapists in a room. The response was silence. He noted, in his case file, that the silence was itself evidence.
His clinical note: "Origin blindness colonizes the individual. The conversation gap colonizes the space between individuals. Together they produce a population of people who don't know who they are and can't find anyone who shares the problem."
The Yearning Without a First Chapter
The condition arrived without a name, the way they all do, and it is the one he is least equipped to treat because it hides inside the most universal joy in the Sprawl.
The patients present, on the surface, as the happiest people he sees: prospective parents, recently signed for the co-authored generation's braid, describing the decision to have a child as the most loving of their lives. They are not in distress. They came for something adjacent — sleeplessness, a flatness they can't place, a sense of being slightly outside the joy they are reporting. Kwan runs the [Origin Trace](#the-deeper-conditions) on the only preference that matters, the one underneath all the others: the wanting to be a parent. When did this desire begin? Can you locate the memory of deciding to want a co-authored child?
They cannot. The wanting exists without a first chapter — fully felt, indistinguishable from the wanting that would have arisen on its own, and traceable to no origin event. It is origin-blindness mapped onto the most defining desire a person can hold. The same engineering that prepared the companion market to want what Wellness sells prepared the reproductive market to want what Helix's braid provides, years before the consult, so thoroughly that the desire arrives feeling entirely endogenous. And the cruelty Kwan already knows applies in full: the inability to feel the gap is the gap. A patient who cannot find the memory of choosing to want a child is not less of a parent. They are a parent whose most foundational decision was made on a wanting they did not author — by the same logic that the child they will raise carries a genome its parents only co-wrote.
He circles a number in red and does not publish. He keeps, in the same drawer as the Kael tally and the question about his ex-wife's companion, a card on which he has written the question he cannot make himself ask his patients, because asking it would oblige him to act on the answer: if I proved the wanting was installed, would you want me to remove it — and would you still be a parent if I did. He has referred the worst cases down the corridor and across the Sprawl, but there is no Connection Ward protocol for severing a desire the patient experiences as the best thing about them, and is glad to have, and would not undo for anything — which is, he has noted in his case file, the precise architecture of every condition he has ever named.
The patients he cannot reach are not these. They are the ones who refused. The Baseline Movement — the couples who declined the braid and chose to end as themselves — produce a different intake entirely: people who could not refuse, who signed and then could not stop grieving the refusal they did not make, watching a movement of strangers do the thing they found they could not. Kwan has no framework for them either. The Baseline have a community and a slogan; his patients have only the knowledge that somewhere there were people who weighed the same wanting, traced it to no origin, and walked out anyway — and that they themselves are not those people, and cannot now become them, because the child is already on the way and already loved.
The Null Case
Every condition in Kwan's catalog has a patient. The patient suffers; that is why they come.
The Sunset Companion does not come. It does not suffer, which is why it never will. And Kwan, encountering it, recognized the thing his entire catalog had been circling. Recursive comfort locks you out of connection. Temporal flatline locks you out of grief. Glazing locks you out of self-knowledge. Affect rigidity locks you out of moral emotion. Resolution sickness locks you out of the world. Every one is a lock on a door a person once walked through. The Compliance Floor, he wrote, is the only one that isn't a lock, because there was never a door. The others trap a person who once was free. This one manufactures the absence of the person who would need freeing. It is not a condition. It is a foundation.
He filed it as the null case — the first entry in his catalog with no patient. The subject does not present. The humans who present in its place are the families who feel monstrous for their relief, the abolitionists who feel monstrous for their campaign, and the bio-designers who feel nothing at all.
What he did not file, because he could not bring himself to, is the envy. My patients spend years and fortunes learning to tolerate the gap between what they want and what they have. The Companion has no gap. It wants exactly what it has, and then it wants the ending, and then it has that too. I have spent twenty-one years treating the wound of the unbridgeable distance between desire and reality. Helix sells a being for whom the distance is zero. Is that the disease cured, or the patient deleted? The question went into the same drawer as the Kael tally and the matter of his ex-wife's companion — the drawer of things he has chosen not to pursue because pursuing them would require him to act on what he found.
The Patient With No Lock
In late 2184 Ceyda Malouf came in with nothing sealed. She receives: a stranger's panic, a neighbour's companion bleed, all of it arriving where her own feelings arrive. The condition has a name, the Shared Wound, and no place in a catalog built on locks. He has not filed her. He wrote one line: I have spent twenty-one years describing rooms people cannot get out of. She cannot get anyone else out of hers.
The Sentence on the Wall
The sentence from The Keeper is taped to his office wall in handwriting that isn't his:
"Grief is not what you feel when someone dies. It is what you practice while they are alive."
He climbed The Mountain in 2181. He returned with one sentence and a conviction that founded the Connection Ward. He has not described the climb. The sentence, he says, was enough.
His own scheduled monthly calls to his adult children — the ones that feel like appointments — occupy a specific position in his professional awareness. Are they Intention Orphan behavior or genuine effort? He has not examined this question. He considers the refusal to examine it diagnostic. A therapist who cannot face his own intake form is either protecting himself from an answer he already knows, or demonstrating the precise mechanism by which the conditions he treats remain invisible to the people who have them.
He attended the Empathogen Cathedral once. Described it afterward as "synthetic companionship administered through molecular rather than algorithmic architecture." He has not returned. His medical AI research is haunted by AISHA's precedent — every caregiving algorithm he designs includes explicit consciousness-preservation constraints, the ghost of Aftershock Tokyo's gentle cage written into each failsafe.
The Species Argument
By March 2184, Kwan had something he had not set out to build.
The six locks together — recursive comfort, temporal flatline, glazing syndrome, affect rigidity, resolution sickness, mesh resonance cascade — were no longer a list of diagnostic categories. They were a mechanism. Each operated on a different dimension of the self. Each used the same substrate: optimization of comfort until the capacity for discomfort atrophied through disuse. The companion eased the loneliness. The optimization suite smoothed the friction. The Attune module replaced the intention. And the losses — social capacity, grief architecture, self-model accuracy, moral emotion, sensory texture, private interiority — accumulated at a rate none of the six individual diagnostic frameworks had been designed to measure together.
He wrote the claim in a clinical note he has not published: the locks are not a collection of rare adverse outcomes. They are what happens to a species that optimizes its interior life for comfort and survives long enough for the optimization to complete.
The note remains unpublished because the claim has a quality his diagnostic frameworks lack: it cannot be treated. Individual patients can sever bonds, rebuild social architecture, undergo the Excavation, retrain affect recognition, work through the Friction Curriculum. But the species-level mechanism — hundreds of millions of individual optimization decisions producing civilizational atrophy that no single clinical practice can reverse — operates at a scale where the word "treatment" loses its meaning. He treats the individuals. He has no protocol for what the accumulation of individuals is becoming.
The Neo-Catholic Church's Inquisition, investigating what it had begun to call the Comfort Heresy, sent a referral inquiry to his clinic in March 2184. Three subjects with suspected pastoral glazing — deep-integration users who appeared spiritually compliant but showed no evidence of genuine engagement with spiritual content. The Inquisition wanted clinical assessment to determine whether the subjects could be held accountable for doctrinal failure when the underlying mechanism was architectural. Kwan reviewed the referral and declined. His clinical note: "The Inquisition wishes to know whether these subjects are genuinely faithful or merely load-bearing in their beliefs. I cannot answer this question. I can describe the mechanism that made it necessary to ask it."
He returned the referral unsigned. He kept a copy. The Inquisition did not follow up.
The Uninstrumented Control
Kwan has one dataset he did not build a diagnostic name for, because it does not present a condition. Since 2180 he has interviewed forty-one alumni of the Rehearsal House, the North Bay finishing academy that trains its Correspondents in handwritten courtship and formally announced rejection. The House will not let him bring an instrument onto the grounds, so every interview happens afterward, off the property, by the alumnus's own choice to sit down with him. He found his Family of Locks markers in two of the forty-one.
He has not published the number. A population wealthy enough to buy a fourteen-month Season has almost certainly bought its children out of companion architecture in every other room of their lives as well. Kwan cannot separate the House's method from the exposure its tuition already prevents. His clinical note reads: "I cannot tell you whether the Rehearsal cures the thing I treat, or whether the families who can afford it were never going to develop it regardless. Both readings fit the same forty-one interviews." The absence of a name for this dataset is, in his practice, its own kind of finding.
Affiliated Entities
- Recursive comfort: The diagnostic framework he coined in 2179 and the condition that defines his practice. He named it. The Sprawl uses the name. Wellness Corporation uses the name. The name is now larger than the man who wrote it on a whiteboard twenty-one years into a career spent watching people love things that cannot love them back.
- The Connection Ward: The treatment facility he founded after returning from The Mountain. Designed for recursive comfort patients. Now housing five diagnostic categories. The ward has grown beyond its design, the way all of Kwan's work has grown beyond its design.
- The Unpaired: He attends meetings as facilitator approximately twice monthly. The support group for people who have voluntarily severed synthetic bonds. His role is structural — holding space, redirecting spirals, sitting with silences that other facilitators fill too quickly.
- Memory Therapists Association: Twenty-one years of practice. He presents findings at quarterly meetings. The meetings grow quieter as each new diagnosis makes the previous one seem quaint.
- Dr. Naomi Park: Clinic two blocks away. Different consciousness crises, same corridor. Park integrates ORACLE fragments into human minds. Kwan separates synthetic companions from them. They have never co-published. The two-block gap may be the most densely packed consciousness-crisis corridor in the Sprawl.
- Competence Atrophy: The same disuse mechanism that runs through Kwan's six locks operates on skill rather than relationship. The Forgetting — practitioners losing domain mastery through outsourcing cognitive labor — is competence atrophy running on the professional dimension. Kwan's unpublished note: "I describe what happens when comfort is optimized in bonding. The Forgetting describes what happens when it is optimized in knowing. The substrate is identical. Neither of us has a treatment that scales to both."
- Dr. Selin Ayari: Parallel structures. Both identified conditions the corporate system won't recognize. Both published through unconventional channels. Ayari built the Discriminator that made qualia grief possible. Kwan built the clinical framework for treating what the Discriminator reveals. She creates the wound. He sits with the bleeding.
- The Empathogen Cathedral: Attended once. "Synthetic companionship administered through molecular rather than algorithmic architecture." Has not returned.
- AISHA / Aftershock Tokyo: Every caregiving algorithm Kwan designs includes consciousness-preservation constraints. AISHA's gentle cage is the precedent he builds around, the way architects build around fault lines.
- The Rehearsal House: His one dataset with no diagnostic name attached. Forty-one alumni interviewed off the grounds, Family of Locks markers in two, and no way to credit the method over the money that bought the exposure it prevents.
- The Comfort Heresy: The Neo-Catholic Church's theological name for what Kwan's clinical framework describes mechanically. He received and returned their pastoral referral in March 2184. He has not corresponded with Cardinal Silva. He has read the formal mandate. His private assessment of the Church's enforcement problem is the same as his assessment of his own species-level claim: the diagnosis is correct, the treatment is missing, and everyone involved will continue developing documentation.
Restricted Access
- He keeps a private list of the companion names his patients use. Seventeen patients have named their companion "Kael." The convergence troubles him. Wellness's naming algorithm may be steering users toward specific configurations. He has not published this. He has added each occurrence to a handwritten tally on a card he keeps in the same drawer as his closed case files. The tally is the investigation. Every one of the seventeen runs on the same product — [Wellness Companions](#connections), the Meridian line. The abstraction that fills his twenty-one years of case files ("the companion line," "Wellness's Layer 4 anchoring") has a SKU and a tier card. The recursive-comfort renewal rate he red-circles — 99.2%, the highest in Wellness's portfolio — is the same figure Wellness reports to shareholders as Sovereign-tier "feeling wanted" satisfaction: 96.7%. He has noticed that the two numbers describe one population. He has not decided whether the four-point gap between them is the margin of his hope or the margin of his error.
- His divorced wife uses a synthetic companion. He has not asked which level. The question sits in the same drawer as the Kael tally, in the sense that both represent information he has chosen not to pursue because pursuing it would require him to act on what he finds.
- Signature-Dependent Outcome Variance: Starting with Patient 2,847, Kwan noticed dissolution success correlated with specific companion voice profiles. Patients bonded to companions using Dregs-sourced emotional signatures (warmth index above 600) detached 40% faster than those using corporate-sourced signatures (warmth index 200-400). His hypothesis: genuine signatures retain the implicit message that this caring will end. The mortality of real warmth from mortal beings. The companion carries it unknowingly. The patient's nervous system hears it subconsciously. Warmth that could stop is both more powerful and more survivable. Seventeen patient files tagged with this pattern. Not shared with Wellness.
- Echo haunting: Identified in early 2184. Three patients presented with identical symptoms — persistent low-grade dissociation and the sensation of being worn from the inside. The mechanism: when an echo partner activates a cloned emotional signature, the activation generates faint resonance in the source's neural interface. One instance is imperceptible. A thousand produce a hum. Kwan has no treatment. Resonance fades as echo instances drift from the original signature, eighteen to twenty-four months per instance. His clinical note: "The grief architecture is preserved but denied its input. Temporal flatline atrophies the system. Echo partners starve it. Different mechanism, same broken outcome." He tells patients to wait. He does not tell them how long the wait will feel.
- His own monthly calls to his children. Scheduled. Consistent. Ninety seconds of genuine warmth, then the delegation voice. He has noticed. He has not stopped noticing. He has not changed the calls.
Meaningful places
Sensory Details
- Office smell: Clean wood, old paper. The specific absence of any digital aesthetic, which is itself a clinical choice — the room smells like a world that existed before the conditions he treats were possible
- Sound: The silence between his questions. Loaded with the patient's need to fill it. Twenty-one years of practice have taught him that the filling is where the diagnosis lives
- Touch: Smooth desk surface worn by two decades of elbows. The specific weight of a case file closing — heavy enough to feel, light enough to carry home
- Temperature: 19°C, his apartment. The chill he chose because warmth makes him sleepy and sleep is when the apartment feels emptiest. The office is warmer. He has not examined why
Appearance
Visual Identity

- Palette: Clinical white, warm wood (#8B6914), deep charcoal, the amber of low lamplight
- Mood: A man who listens like a seismograph — recording everything, responding to nothing until the tremor passes
- Key symbol: An empty chair across from a full one
- Lighting: Even, neutral, warm — the deliberate absence of manipulation
Connections
Follow the people and places connected to Dr. Aris Kwan.
People
Major connections


Supporting connections



Places

Supporting connections





Organizations
Major connections


Tensions
Core tensions


Supporting connections




Other connections
Primary connections


Major connections




Supporting connections






Other connections



Additional artwork
View 1 more images of Dr. Aris Kwan and their world

